

Open-heart surgery: how long it lasts, what really happens, and life afterwards
Three to six hours in the operating theatre, about a week in hospital, six weeks for the breastbone to knit back together. Here is exactly how an open-heart operation unfolds, the success figures as they are published in the national registries, and the signs that should bring you back to hospital after you go home.
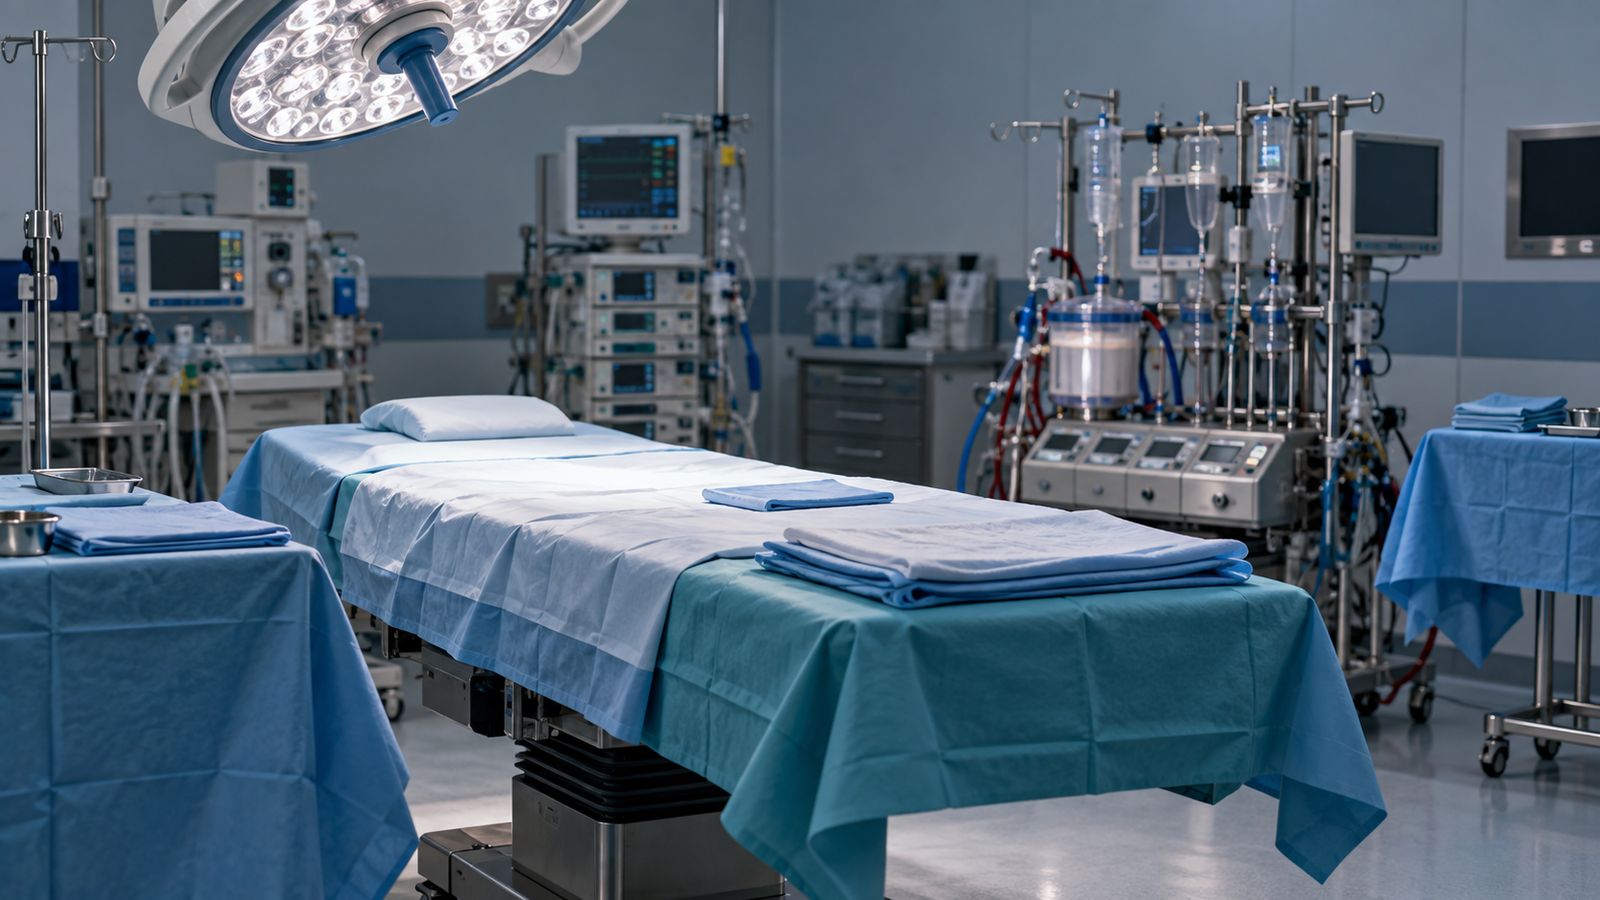
"How long does the operation take?" "What is the success rate?" "What will I not be allowed to do afterwards?" These are the three questions that come up most often, both in consultation and in search engines. Here are the answers, with the figures as they are published in the national registries, what they do not tell you, and practical guidance for the weeks after you get home.
Key figures
- 3 to 6 hours
- This is the usual length of a bypass operation in the operating theatre. The heart-lung machine, for its part, only runs for part of that time. NHS and Cleveland Clinic, 2025
- 1,06 %
- In-hospital mortality for an isolated aortic valve replacement in the United Kingdom in 2018, compared with 5.28% in 1996, across 79,173 patients. NACSA national registry, 2023
- 1 week
- In hospital on average, including 24 to 48 hours in intensive care, when recovery is straightforward. NHS, 2025
- 28 %
- Fewer heart attacks in patients who follow cardiac rehabilitation, across 107 trials and 26,886 participants. Cochrane, September 2026
"Open-heart surgery", what it actually means
The phrase is misleading. It does not mean that the heart itself is opened every time, but that the chest is opened and that the circulation of the blood is handed over to a machine during the procedure. The standard approach is the sternotomy: a vertical incision in the middle of the chest, about fifteen centimetres long, after which the breastbone is cut along its length with a sternal saw and held apart to expose the heart. At the end of the operation it is closed again with eight to twelve stainless steel wires, which stay in place permanently and are only removed if there is a complication.
Three main families of operations use this approach: the bypass, which goes around a blocked artery of the heart, valve surgery, and surgery of the aorta. These are different procedures, but the days that follow are very similar, because it is the same chest that has to heal.
Open-heart surgery in Tangier: when it is needed
How long an open-heart operation takes
For a bypass, the British NHS and the Cleveland Clinic both state three to six hours. A French-speaking university centre, the Geneva University Hospitals, gives a shorter range, two to four hours depending on the number of bypass grafts to be done. For an aortic valve replacement, the Cleveland Clinic gives two to four hours.
What reassures families most lies elsewhere. The time spent on the heart-lung machine is much shorter than the total time in theatre. In a study of isolated bypass operations, the median time on the machine was about 72 to 82 minutes, and the heart was stopped for only about forty minutes. In a four-hour operation, most of the time is therefore taken up by the anaesthetic, positioning the patient, taking the grafts and closing the chest carefully.
Warn your family: between going down to theatre and coming back to intensive care, the wait is almost always longer than the stated length of the operation. That is not a bad sign, it is simply how an operating day works.
What the heart-lung machine does while the heart is stopped
Cardiopulmonary bypass, which is the medical name for this machine, temporarily takes over from the heart and the lungs. The blood is diverted out of the body, an oxygenator adds oxygen to it and removes carbon dioxide, then a pump sends it back into the body. The machine also controls the temperature of the blood.
During this time the heart is deliberately stopped by a solution called cardioplegia, so that the surgeon works on an organ that is still and free of blood. That is what makes precision possible. Once the procedure is finished, the machine is disconnected and the heart starts again. The Cleveland Clinic notes that the risk of complications is lower when the time spent on the pump stays under three hours, which is why surgical teams always try to keep it as short as possible.
Not every procedure needs this machine. TAVI, which places a valve through a catheter without opening the chest, is done without cardiopulmonary bypass and without stopping the heart, in a patient who is simply sedated.

Waking up: 24 to 48 hours in intensive care, then the ward
When you wake up you will be in the intensive care unit, with a breathing tube that is removed as soon as breathing on your own is safe, drains in the chest, drips and continuous monitoring of your heart rhythm. The NHS gives one to two days in intensive care, the Cleveland Clinic about twenty-four hours, before the move to a ward.
The total length of stay in hospital is around a week. The British national registry gives an average of 7.8 days after a first bypass, with real differences between hospitals, from 6.2 to 11 days. After the age of 80, the median stay goes from seven to nine days: recovery is slower, not only the risk higher.
Two habits learned in hospital are worth keeping at home. The first is to hold a cushion firmly against your chest when you cough: it hurts, but coughing is essential to clear the lungs. The second is to get up using your elbow rather than pushing on your hands, to spare the breastbone.
The success figures, and what they do not tell you
Countries that keep a national registry publish their results. In the United Kingdom, across about 34,000 heart operations a year, the NACSA registry report gives the following for 2018-2019:
- 0.74% in-hospital mortality after a planned bypass, which is about 99% survival.
- 1.32% after a bypass performed as an emergency.
- 0.9% after an isolated aortic valve replacement before the age of 75, and 1.2 to 1.3% after 75.
- 2.59% for heart surgery as a whole, emergencies included, compared with 3.61% twelve years earlier.
A study published in 2023 covering 79,173 isolated aortic valve replacements gives the best measure of this progress: 1.06% mortality in 2018, compared with 3.28% in 2000 and 5.28% in 1996. In one generation, the risk has been divided by five.
These figures call for a caution that few websites take the trouble to write down. They are national averages, calculated on selected patients who were operated on after assessment. They are not individual probabilities and they are never a promise of a result. The same registry shows this clearly when it sorts patients according to their predicted risk: mortality ranges from 0.7% in low-risk patients to 6.1% in high-risk patients. Your own figure is calculated before the operation, from your age, how well your heart is working, your other illnesses and whether or not the procedure is urgent. Ask for it, it is part of the information you are entitled to.
A final word about Morocco: no national heart surgery registry publishing its results was found. The figures quoted here are therefore British, for want of published and verifiable Moroccan data.
After 70, and with diabetes: what changes
Age increases the risk, but less than people imagine. In a British and Irish national series of 227,442 patients aged 70 and over, in-hospital mortality was 3.0% between 70 and 79 years and 4.4% beyond 80. More importantly, in these patients in their eighties it halved over the period studied, falling from 8.9% to 4.4%, while their share of all heart surgery rose from 4.1% to 10.8%. In other words: more and more older patients are being operated on, and with better and better results.
Diabetes, for its part, weighs on two counts. First on the choice of technique: the 2024 European guidelines, endorsed by the American and European surgical societies, place bypass surgery rather than angioplasty at the highest level of evidence in diabetic patients with disease in several arteries. This is not a matter of school of thought, it is a documented survival benefit.
Then on healing. Deep sternal wound infection occurs in 0.6 to 5% of heart operations, and diabetes is among the risk factors identified, along with smoking, obesity and age. This is the practical point to remember: keeping your blood sugar under control before and after the operation directly protects the strength of your breastbone.

The six weeks of the breastbone, and the movement that matters more than the weight
The breastbone has been cut and it has to knit back together. The timescales given vary: six weeks for healing and three months for consolidation considered definitive in a French cardiac surgery document, eight weeks for the Cleveland Clinic, three months for a London hospital. Remember the range: six weeks for most things, three months for heavy exertion.
The weight limit, on the other hand, is the subject of a disagreement that it is more honest to tell you about than to hide. Depending on the hospital, it ranges from 4.5 kg to 9 kg, over a period of six to twelve weeks. A review published in 2016 showed that these thresholds rest on expert opinion rather than on direct evidence, and points out a disconcerting fact: a simple cough exerts about 27 kg of force on the breastbone, and a sneeze about 41 kg, which patients withstand every day.
What matters is therefore not so much the number of kilos as the way you move. The most useful principle is to keep your elbows close to your body, as if they were enclosed in a tube, and to avoid pushing, pulling and carrying at arm's length. Ask your team for the exact instruction, because it varies from one centre to another.
In practical terms, here is what patient leaflets advise against before six weeks, and often before three months for heavy exertion:
- Carrying shopping heavier than four to five kilos, or carrying a child.
- Vacuuming, digging, mowing the lawn, trimming a hedge, painting, washing the car.
- Working with your hands above your head, or keeping your arms raised for a long time.
- Walking a dog that pulls on the lead, pushing a full shopping trolley.
- Standing still for more than a quarter of an hour.
- Any activity that brings on pain in the breastbone: leave it aside for a few days, then take it up again more gently.
One question comes up constantly and deserves to be addressed as it is: prayer. No medical study looks at prostration after a sternotomy, and it is not for a surgeon to settle a religious question. What is documented is physical: the precautions concern taking weight through the arms and spreading the elbows. Getting up from a low position by pushing on your hands, or taking the weight of your body on your forearms, falls within what teams ask you to avoid in the first weeks. It is for your surgeon and your physiotherapist to adapt this with you, according to how solid your breastbone is.
Walking, driving, working, travelling
Walking is the best exercise for this period, and it starts early: getting up and taking your first steps happen the day after the operation, with the physiotherapist. At home, the British Heart Foundation advises starting with two minutes of walking if that is all you can manage, every day, until you reach fifteen to twenty minutes at a stretch by around the fourth or sixth week. On flat ground at first, without chasing performance.
On driving, countries do not say the same thing. The French Assurance Maladie and the British NHS give about four weeks, with your doctor's agreement, and three months for a professional licence. The Cleveland Clinic recommends rather six to eight weeks, the time needed for the breastbone to heal and for concentration to come back. No official Moroccan rule was found on this point: it is for your surgeon to tell you when to get behind the wheel again.
For work, the French reference durations after a bypass, set following advice from the Haute Autorité de Santé, are clear:
- Sedentary work: 42 days, that is six weeks.
- Light physical work: 56 days, that is eight weeks.
- Moderate physical work: 70 days, that is ten weeks.
- Heavy physical work, above 25 kg: 90 days, that is three months.
These durations are guides for most patients, not obligations. The same document points out that opening the breastbone limits heavy physical work with the arms, and that part-time hours or an adjustment to the job can be considered. The exercise stress test, carried out four to seven weeks after the operation, helps with the decision.
For flying, a short flight is generally possible from about ten days onwards when recovery is straightforward, the time needed for the remaining air in the chest to be absorbed. For a long-haul flight, most teams ask you to wait six to eight weeks, because of the risk of a clot in the veins of the leg. In every case, the go-ahead is given at the follow-up appointment.
Cardiac rehabilitation, the treatment least talked about
Yet it is the one with the strongest evidence. The Cochrane review updated in September 2026 brings together 107 randomised trials and 26,886 people with coronary heart disease. In those who follow exercise-based rehabilitation, heart attacks fall by 28% and hospital admissions from all causes by 35%, with an improvement in quality of life covering physical fitness, vitality, social life and mental wellbeing. Another recent finding, useful when the centre is far away: home-based and remote programmes prove just as effective as centre-based programmes.
In France, the Haute Autorité de Santé defines rehabilitation as something broader than sport: retraining for physical effort, correcting risk factors, adjusting treatment, education, psychological support and preparing for the return to work. It specifies that the healing of the breastbone must be taken into account in exercises that involve the chest and the arms. After the programme, the prevention target is thirty minutes of moderate activity five times a week.
One point of interpretation: these Cochrane figures relate to coronary heart disease, so to patients who have had a bypass. They cannot be transferred as they are to valve surgery, even if the value of keeping moving is in no doubt for anyone.
Your mood matters too, and it can be treated
Feeling low, crying for no reason, sleeping badly or losing interest in everything in the weeks after heart surgery is common. A meta-analysis of 16,501 patients found depressive symptoms in 15 to 33% of people operated on for a bypass, depending on the scale used, which is about one patient in five.
This is neither self-indulgence nor weakness, and it is not without consequences: the official French document on returning to work explicitly names anxiety and depression among the factors that lengthen the return to normal life. There is therefore everything to gain from talking about it to your team rather than keeping it to yourself out of embarrassment. Psychological support is an integral part of rehabilitation.
Mechanical valve or biological valve
When the operation involves replacing a valve, this question always comes up. The two main sets of guidelines do not set the same age: the American ones from 2020 lean towards a mechanical valve before 50, the European ones from 2025 before 60, and both agree on a biological valve beyond 65. Between these limits, the discussion is open.
The trade-off is simple to understand. The mechanical valve lasts a very long time, but requires anticoagulant treatment for life, with regular blood tests and permanent precautions. The biological valve avoids this long-term treatment, but generally lasts fifteen to twenty years according to the NHS, with the possibility of a further operation later on. In British practice, 82.5% of isolated aortic valve replacements are done with a biological valve, and this proportion rises to 98.2% after the age of 70.
The most important point lies elsewhere: in both sets of guidelines, the highest-level criterion is not age, it is the decision shared with you, after full information. Your job, any plan for a pregnancy, your ability to follow anticoagulant treatment and the possibility of operating again later count as much as your date of birth. As for TAVI, placing a valve through a catheter, it is considered mainly in older patients or in those for whom surgery would be too risky.
Read also: severe aortic stenosis, symptoms and when to operate
The signs that should bring you back to hospital
One figure on its own explains why this list is essential: the median time for a deep sternal wound infection to appear is fifteen days. That is to say after you have gone home, when nobody is watching the scar for you any more.
Contact your surgeon or your doctor without delay if you notice:
- Redness, discharge or pus at the scar.
- Pain in the scar that comes back or gets worse.
- A feeling that the breastbone moves, cracks or clicks when you move or cough.
- A fever.
- Palpitations. They are common after this type of surgery, of the order of 15 to 30% after a bypass and 30 to 40% after valve surgery, most often in the first five days, and they respond well to treatment, but they do need to be seen.
Call the emergency services immediately, 141 for the SAMU or 15 for Civil Protection, if you have chest pain that does not go away, pain that spreads to the arm, the neck or the jaw, sudden breathlessness, or signs of a stroke such as difficulty speaking, weakness in one arm or the face drooping on one side.
Dr Tber, cardiovascular and thoracic surgeon in Tangier, operates on and follows up his patients with his team at the Clinique Riad Marshan, from the first consultation through to the check-ups that follow the operation. A question about an operation that has been proposed, or a second opinion before deciding, can be discussed in consultation.
Read also: recovery after a bypass, week by week
Frequently asked questions
How long does an open-heart operation take?
What is the success rate of an open-heart operation?
Can the heart be operated on at 75 or 80?
How many days do you stay in hospital?
What is not allowed during the first few weeks?
When can you drive again and go back to work?
How can you pray after open-heart surgery?
Mechanical valve or biological valve, which one to choose?
Is it normal to feel depressed after the operation?
Sources and references
External resources, opened in a new tab.
- Coronary artery bypass graft: how it's done, recovery, complications NHS, reviewed on 3 July 2025
- Heart valve replacement: how it's done and recovery NHS, reviewed on 17 July 2025
- National Adult Cardiac Surgery Audit, 2020 summary report (2016-2019 data) NICOR / HQIP, British national registry
- Trend and early outcomes in isolated surgical aortic valve replacement in the United Kingdom (79,173 patients) NACSA registry, published in 2023
- Cardiac surgery in patients aged 70 and over, United Kingdom and Ireland national series (227,442 patients) Published in 2021
- Multisociety endorsement of the 2024 European guideline recommendations on coronary revascularization ESC 2024, endorsed by the AATS, STS and EACTS
- Deep sternal wound infection after cardiac surgery Journal of Thoracic Disease, 2018
- Exercise-based cardiac rehabilitation for coronary heart disease (107 trials, 26,886 participants) Cochrane, September 2026 update
- Sick leave: coronary revascularisation, reference durations Assurance Maladie and Haute Autorité de Santé
- Referral criteria for cardiac and vascular rehabilitation Haute Autorité de Santé, 22 October 2024
- Prevalence of depression in coronary artery bypass surgery, systematic review and meta-analysis (16,501 patients) Journal of Clinical Medicine, 2020
- Postoperative atrial fibrillation after cardiac surgery, systematic review of 52 studies Published in 2025
- Sternotomy and Cardiopulmonary bypass, patient information sheets Cleveland Clinic
- Postoperative instructions after cardiac surgery, patient leaflet Unité de chirurgie cardiaque de l'Artois
- Sternal precautions following cardiac surgery and Keep Your Move in the Tube Ohio State University Wexner Medical Center and Proceedings (Baylor University Medical Center), 2016
- Fitness to fly for passengers with cardiovascular disease British Cardiovascular Society, Heart 2010
Readable also
On the blog
Cardiologist or cardiac surgeon in Tangier: who should you see, and when?
Both look after the heart, but they come in at different stages. Here is how to know which one to turn to, and why most patients end up seeing both.
Read
Blocked artery in the leg: calf pain when walking, the tests, stent or bypass
Calf pain that always appears after the same distance and goes away within a few minutes of rest is the first sign of a blocked artery in the leg. Here is how the diagnosis is made, what it says about your heart, and when an operation is genuinely discussed.
Read