

After coronary angiography: stent or bypass, how is the next step decided?
A coronary angiogram does not just show the state of your arteries, it steers the whole treatment. Here are the three possible outcomes and the criteria that tip the balance towards a stent or towards a bypass.
Written by Dr Mohamed el Amine Tber, cardiovascular surgeon in Tangier
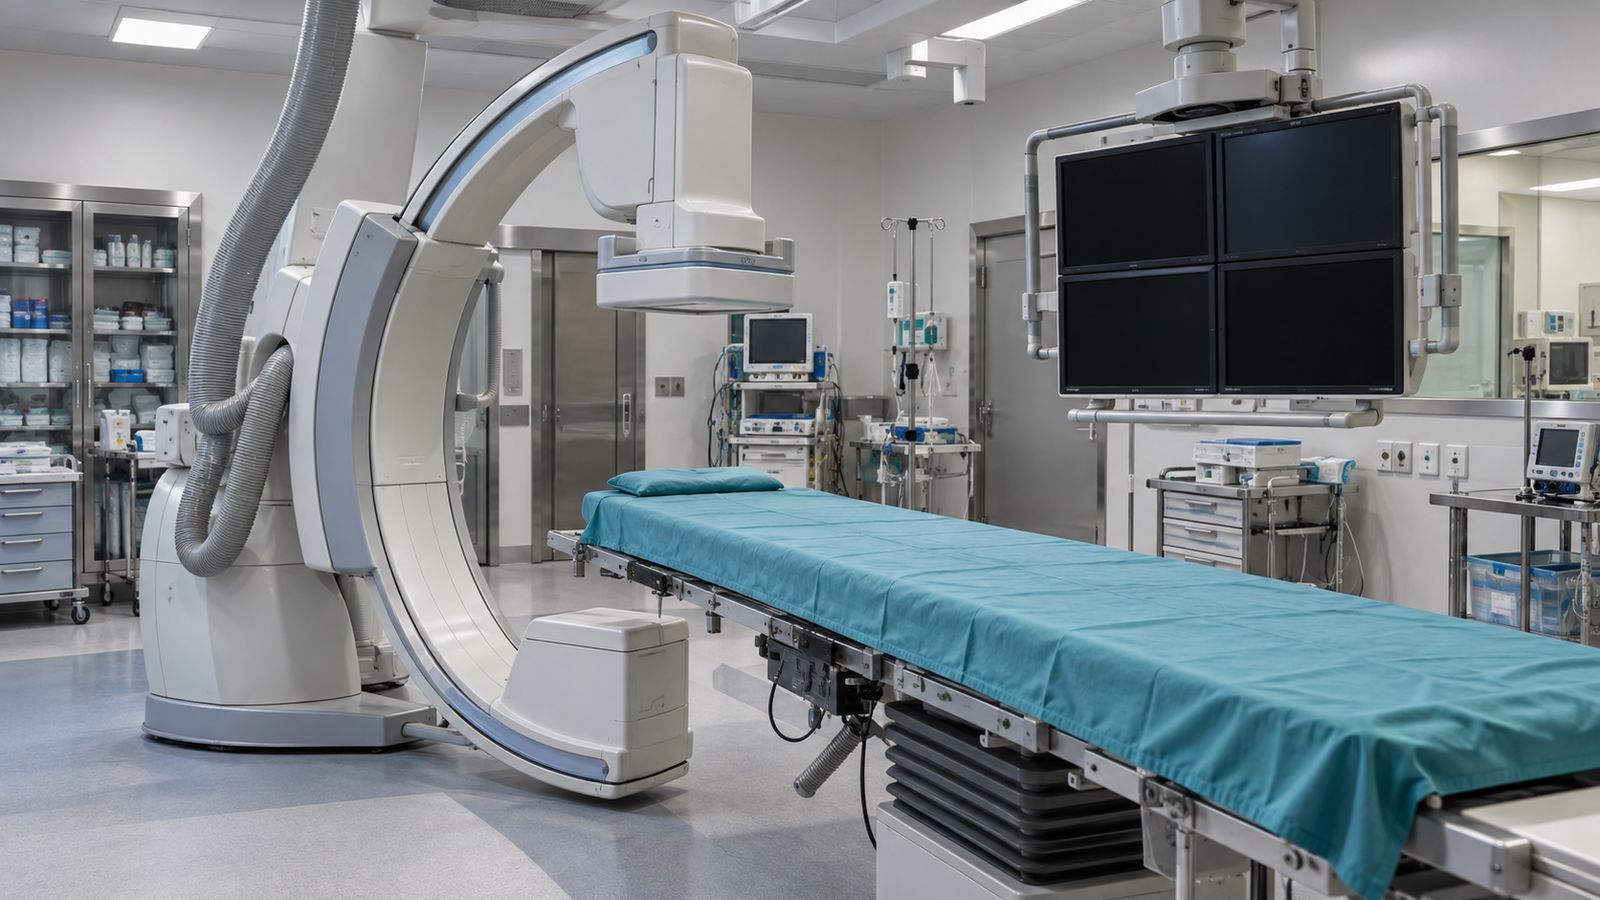
A coronary angiogram is often experienced as the moment of truth. It partly is, but it is not an endpoint: it is where a decision starts. Once the images are in, the question becomes what to do next, and the answer is not the same for two patients whose arteries look alike.
Key figures
- 30 min to 2 h
- This is the usual length of a coronary angiogram, and patients generally go home the same day. NHS
- 1 week
- After a planned angioplasty with a stent, you avoid driving for one week. NHS
- 18,7 %
- In people with diabetes and several diseased arteries, the risk of death, heart attack or stroke at 5 years was 18.7% after bypass, versus 26.6% after stents. FREEDOM trial, New England Journal of Medicine, 2012
- 1,6 %
- Through the wrist, serious bleeding fell to 1.6%, versus 2.3% through the groin, in patients treated for an acute coronary syndrome. MATRIX trial, The Lancet, 2015
What exactly a coronarography shows
The test involves injecting a contrast dye into the arteries that feed the heart muscle, the coronary arteries, then filming them under X-ray. It answers precise questions: which arteries are narrowed, by how much, over what length, exactly where, and whether blood is still finding its way round through collateral vessels.
What a coronary angiogram cannot tell you on its own: how strongly your heart contracts, the state of your valves, whether you could withstand an operation. Those come from the echocardiogram, the blood tests and the consultation.
After the test: rest, driving and returning to work
A simple coronary angiogram generally takes 30 minutes to 2 hours, and most patients go home the same day. Today it is most often done through the artery in the wrist, which the European guidelines make the first choice because it carries less risk of bleeding than the groin.
- On the day of the test : rest for the remainder of the day, and do not drive yourself home.
- The next day : most usual activities can resume, with no intense effort or heavy lifting for a few days.
- At the puncture site : a small bruise is common. Bleeding that does not stop despite pressure, swelling that gets bigger, or pain, paleness or numbness in the hand or leg means you should contact the team straight away.
- If a stent was fitted : UK advice is not to drive for one week after a planned angioplasty, and returning to work is often possible after one week. After a heart attack, the timescales are longer.
Never change the medication prescribed at discharge yourself, especially antiplatelet drugs after a stent: stopping them too early exposes you to a clot forming in the stent.

The three possible suites
1. Medical treatment alone
It is the most common outcome, and often the best. When the narrowings are moderate or few in number, well-conducted treatment associated with cessation of tobacco and control of diabetes, cholesterol and blood pressure results in lasting results. Not being operated is not a failure, it is a result.
2. Angioplasty with stent placement
The interventional cardiologist opens up the narrowed segment with a balloon and leaves a small metal scaffold behind, the stent, which holds the artery open. The hospital stay is short, recovery quick, and it can sometimes be done straight after the angiogram.
3. Coronary artery bypass
The surgeon takes a vessel, most often the internal mammary artery or a vein from the leg, and builds a new route around the diseased segment. It is a bigger operation, but it lasts longer where the disease is extensive. It is set out in detail on our page about bypass.
Criteria that make one side or the other tilt
| Folder element | Rather, it is oriented towards |
|---|---|
| A single artery affected, short and accessible lesion | Stent |
| Three arteries affected, or common trunk damage | Bypass surgery |
| Diabetes with multiple arteries | Bypass surgery |
| Very calcified, long or at a crossing | Bypass surgery |
| Heart function diminished | Discussion on a case-by-case basis, often a bypass |
| Significant Fragility, High Age, Other Severe Diseases | Stent or medical treatment |
No one of these criteria decides on its own. It is the combination that counts, and your own view is part of it.
Diabetes is a good example. In the FREEDOM trial, in people with diabetes and several diseased arteries, the risk of death, heart attack or stroke at 5 years was 18.7% after bypass versus 26.6% after stents, at the cost of slightly more strokes after surgery (5.2% versus 2.4%). It is this kind of result, not the preference of one school of thought, that guides the recommendation.
A decision that is made by several
In complex cases, good practice is to sit the cardiologist and the surgeon down over the same file before anything is put to the patient. That joint discussion avoids two mirror-image mistakes: offering surgery where a simple procedure would have done, and stacking up stents where one operation would have settled the matter for good.
The 2024 European guidelines make it a rule: when bypass and stents are both possible, the case must be discussed by a “Heart Team”, with the interventional cardiologist, the cardiac surgeon and the cardiologist who follows you.
Read also: cardiologist or cardiac surgeon, who to see and when

Questions to ask before accepting
- How many arteries are involved, and which?
- What happens if I don't do anything right now?
- What benefit do you expect, about symptoms and risk?
- What are the risks specific to my case, not the general figures?
- How long is the hospital and the activity stopped?
- What treatment should I take next, and for how long?
A doctor who answers these questions willingly is a good sign. Nobody should sign a consent form without understanding what they are signing.
Prepare for the next round
Whichever option is chosen, a few things improve the outcome: stopping smoking, even late in the day, getting diabetes under control, taking your prescribed medicines without gaps, and flagging any blood-thinning treatment. If surgery is planned, a dental check is often asked for, because a dental focus of infection can jeopardise heart surgery.
If bypass is chosen, recovery follows predictable stages, from leaving hospital to driving and working again.
Read also: recovery after coronary bypass surgery, week by week
After a stent as after a bypass, chest pain that comes back, lasts or comes with sweating means you must call 141 (SAMU) or 15 (Civil Protection).
You come out of a coronary chart and we're talking about surgery? Dr Tber's practice in Tangier takes your file, talks you through the reasoning and gives you a clear opinion, including when that opinion is not to operate. Book an appointment.
Frequently asked questions
How long does a coronary angiogram take?
Is coronarography painful?
Can you drive after a coronary angiogram?
Can we put a stent in the coronarography itself?
Why do I get a bypass when a stent seems simpler?
How long can we wait between the coronarography and the operation?
Sources and references
External resources, opened in a new tab.
- Coronary angiogram: what happens and afterwards NHS
- Recovery after coronary angioplasty NHS
- FREEDOM trial: stent or bypass in people with diabetes New England Journal of Medicine
- MATRIX trial: radial or femoral access The Lancet
- 2024 guidelines on chronic coronary syndromes European Society of Cardiology
- Coronary bypass surgery: the operation and recovery British Heart Foundation
Readable also
On the blog
Coronary angiography in Morocco: cost, CNSS coverage, and what happens after the test
A coronary angiography costs between 8,000 and 15,000 dirhams in Morocco, and up to 30,000 to 45,000 dirhams if a stent is placed at the same time. For CNSS members, the test is one of the conditions covered at 100% after prior approval. What drives the price, the steps, and the three possible outcomes.
Read
Having heart surgery in Morocco when you come from elsewhere in Africa: how much to budget for the operation, the stay and the journey
A heart operation in Tangier costs between 70,000 and 150,000 DH depending on the procedure, or about 6,400 to 13,600 euros. For a patient coming from Senegal, Côte d'Ivoire, Cameroon or elsewhere, you also need to add the journey, the stay and the person accompanying you. Here is the full budget, item by item.
Read